

Question

| A. | Renal Infarct |
| B. |
Renal Calculus |
| C. |
Ureteric Calculus |
| D. |
Renal Carcinoma |


|
Correct Answer � B Explanation |
 |

Ans: B.)Renal Calculus
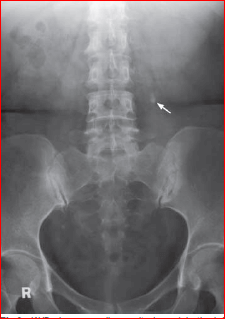
Image shows: Coned KUB shows radioopacities (arrows) over the left renal area which may represent renal stones.
RENAL CALCULUS
-
Renal calculus is a common cause of haematuria, particularly in the presence of loin pain.
-
Renal calculi are composed of crystals and/or aggregated with proteins.
-
The crystal may contain calcium or magnesium oxalate/phosphate (which are radio-opaque and found in the majority of stones) or uric acid/ xanthine (which are not radio-opaque). As a result of this variable composition, the majority (~90%) of renal stones are radio-opaque, hence a KUB is useful as the initial investigation in a patient with suspected urinary calculus.
-
IVU is the key imaging modality for the diagnosis of
-
(1) Suspected urinary tract calculus
-
(2) Radio-lucent calculus which is not visualized on KUB
-
(3) Ureteric calculus may not be demonstrated by ultrasound.
-
Information on IVU which is helpful in the management of patients with renal stone include:
-
1. Size of renal stones.
-
2. Coexisting ureteric obstruction – extracorporeal shock wave lithotripsy (ESWL) may not be possible since stone fragments cannot pass down the ureter.
-
3. Associated renal cortical scarring.
-
If a patient is allergic to an intravenous contrast medium, ultrasound is a good alternative imaging modality for diagnosis.