

Question
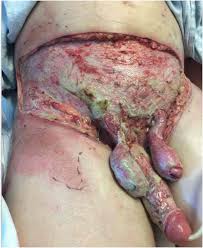
True statement for the following condition shown in image

| A. | Caused by mixed bacterial infection |
| B. |
Bladder diversion required |
| C. |
B/L orchidectomy needed |
| D. |
Anti gas gangrene serum should be given |


|
Correct Answer » A Explanation |
 |

Detailed Explanation:
Anatomical Role
– The scrotum houses the testes, epididymis, and lower spermatic cord structures.
– Infection or necrosis involves superficial and deep perineal fascial layers.
Clinical Reasoning for the Correct Answer
– The image shows black necrotic scrotal skin and swelling, characteristic of Fournier’s gangrene, a necrotizing fasciitis of the perineum and genital region.
– Fournier’s gangrene is caused by mixed aerobic and anaerobic bacteria, including E. coli, Bacteroides, Streptococci, and Staphylococci.
– Early and aggressive surgical debridement is essential, along with broad-spectrum antibiotics covering mixed flora.
Why Option A is Correct:
– Mixed bacterial infection with both aerobes and anaerobes causes tissue necrosis and rapid progression.
Why Option B is Incorrect:
– Bladder diversion (e.g., suprapubic catheter) is not routinely required unless urinary tract involvement or obstruction exists.
– The primary management is surgical debridement and antibiotics, not bladder diversion.
Why Option C is Incorrect:
– Bilateral orchidectomy (removal of both testes) is rarely necessary and only considered if testicular involvement occurs, which is uncommon due to separate blood supply.
– Testes are usually spared in Fournier’s gangrene because the infection affects superficial fascia, not the testicles.
Why Option D is Incorrect:
– Gas gangrene is caused by Clostridium perfringens, treated with penicillin and surgical debridement; anti-gas gangrene serum is outdated and not routinely used.
– Fournier’s gangrene is not classical gas gangrene; thus, anti-gas gangrene serum is not indicated. .
High‑Yield Synopsis:
– Etiology & Pathogenesis
– Fournier’s gangrene is a polymicrobial necrotizing fasciitis of genital and perineal regions.
– Common organisms: mixed aerobes and anaerobes (E. coli, Bacteroides, Streptococci).
– Often occurs in diabetics, immunocompromised, or trauma patients.
– Clinical Features
– Rapid onset of scrotal/genital pain, swelling, erythema, and skin necrosis.
– Crepitus may be present due to gas in tissues.
– Systemic toxicity and sepsis are common.
– Diagnostic Findings
– CT or ultrasound may show subcutaneous gas.
– Laboratory: leukocytosis, elevated inflammatory markers.
– Management & Prognosis
– Immediate broad-spectrum antibiotics covering mixed flora.
– Urgent surgical debridement of necrotic tissue.
– The testes usually spared; orchidectomy uncommon.
– Bladder catheterization only if urinary system involved.
– Mortality can be high without prompt intervention.