
METABOLIC ALKALOSIS
30. PaC02 is 60. Most likely diagnosis?
| A | Metabolic alkalosis with respiratory compensation | |
| B | Mixed metabolic acidosis and metabolic alkalosis | |
| C | Respiratory acidosis with renal compensation | |
| D | Respiratory alkalosis with no compensation |
30. PaC02 is 60. Most likely diagnosis?
| A | Metabolic alkalosis with respiratory compensation | |
| B | Mixed metabolic acidosis and metabolic alkalosis | |
| C | Respiratory acidosis with renal compensation | |
| D | Respiratory alkalosis with no compensation |
• The uncomplicated acid-base disorders, which may be of metabolic or respiratory origin, are classified as being metabolic acidosis, metabolic alkalosis, respiratory acidosis, or respiratory alkalosis.The pH (normal 7.38 to 7.44) determines whether the primary process is an acidemia (pH < 7.38) or an alkalemia (PH > 7.44). (Note that compensation for an alkalosis is always acidosis, while compensation for acidosis is always alkalosis, but in either case, compensation does not bring the pH into the normal range.)
• Bicarbonate levels in metabolic acidosis are <21 mM, while those in metabolic alkalosis are >28 mM. Similarly, with respiratory disorders, examine the Pac02 (normal PC02 is 35 to 40 mmHg arterial, 40 to
45 mmHg venous). in patient with respiratory alkalosis the Pac02 is <35, while with respiratory acidosis the Pac02 is >40.
• Patients with metabolic alkalosis lose acid, and this causes an increase in the blood pH the body compensates for – this increased pH by decreasing the respiratory rate, which increases blood CO2 levels (hypercapnia) and increases the renal excretion of bicarbonate. Causes of metabolic alkalosis include vomiting
(losing gastric acid), increased aldosterone secretion (which causes increased [H· ] excretion by the kidneys), and certain diuretics.
• In contrast, metabolic acidosis increases serum acid (increased hydrogen ion concentration), which decreases serum pH and decreases serum bicarbonate concentration. The causes of metabolic acidosis are broken down clinically into two groups: those with a normal anion gap and those with an increased anion gap. (The serum anion gap is found by taking the serum sodium concentration and subtracting the concentration of two anions, namely chloride and bicarbonate.
• Normally, the anion gap is between 10 and 16 meq/L.) Increased anion gaps result from increased unmeasured anions, such as may occur in the following clinical situations: ketoacidosis (increased beta- hydroxybutyric acid and acetoacetic acid, seen with diabetic ketoacidosis); lactic acidosis (hypoxic conditions); chronic renal failure (uremia); and ingestion of certain substances such as salicylates, ethylene glycol, methanol, and formaldehyde.
• A normal anion gap metabolic acidosis may result from either loss of bicarbonate (diarrhea) or loss of renal regeneration of bicarbonate, seen with renal tubular acidosis type 1 (decreased excretion of titratable acid, i.e., NH and renal tubular acidosis type 4.
• In a patient with metabolic acidosis, the body tries to combat the decreased pH by increasing the respiratory rate (tachypnea), which helps to raise the pH by blowing off CO2 and decreasing the serum CO2 (hypocapnia). The body also compensates through renal mechanisms that increase H excretion and increase bicarbonate reabsorption.
In severe metabolic alkalosis all are seen EXCEPT:
| A | Pulmonary edema | |
| B |
Hypoxia |
|
| C | Hypocalcaemia | |
| D |
Tetany |
Pulmonary edema REF: Harrison 17th edition, chapter 48
With metabolic alkalosis, changes in central and peripheral nervous system function are similar to those of hypocalcaemia; symptoms include mental confusion, obtundation, and a predisposition to seizures, paresthesia, muscular cramping, tetany, aggravation of arrhythmias, and hypoxemia in chronic obstructive pulmonary disease. Related electrolyte abnormalities include hypokalemia and hypophosphatemia.
| A |
Metabolic acidosis |
|
| B |
Metabolic alkalosis |
|
| C |
Hyperkalemia |
|
| D |
None of the above |
By inhibiting salt reabsorption in the TAL, loop diuretics increase delivery to the collecting duct.
Increased delivery leads to increased secretion of K+ and H+ by the duct, causing hypokalemic metabolic alkalosis.
This toxicity is a function of the magnitude of the diuresis and can be reversed by K+ replacement and correction of hypovolemia.
| A |
Hyperkalemic metabolic acidosis |
|
| B |
Hypokalemic metabolic acidosis |
|
| C |
Hyperkalemic metabolic alkalosis |
|
| D |
Hypokalemic metabolic alkalosis |
Neonates with congenital pyloric stenosis develop projectile postprandial vomiting between 2 and 4 weeks of age but may start as late as 12 weeks.
Due to this vomiting they develop hypokalemic hypochloremic metabolic alkalosis.
| A | 1, 2, 3 – True & 4, 5 – False | |
| B |
1, 5 – True & 2, 3, 4 – False |
|
| C |
4, 5 – True & 1, 2, 3 – False |
|
| D |
All are true |
Tumors responsible for ectopic secretion of ACTH are small cell carcinoma, bronchial carcinoid, medullary thyroid carcinoma, pancreatic carcinoma and pheochromocytoma. It can lead to Cushing’s syndrome.
Common clinical features of Cushing’s syndrome are central obesity with moon face, buffalo hump, thin extremities, muscle weakness, diabetes, hypertension, amenorrhea, osteoporosis, poor wound healing and psychosis.
Hypokalemia and metabolic alkalosis is seen particularly in patients with ectopic ACTH secretion. Earliest screening test for diagnosing Cushing’s syndrome is dexamethasone supression test. If its abnormal a high 24 hour urine free cortisol helps in confirming diagnosis. Late night salivary cortisol test have high sensitivity and specificity for Cushing’s syndrome.
In Metabolic alkalosis, which is true about excretion in urine?
| A |
More of NH3 |
|
| B |
Less of aceto acetic acid |
|
| C |
Betahydroxy butyric acid |
|
| D |
Less ammonia |
Metabolic alkalosis is seen in all except –
| A |
Thiazide diuretics |
|
| B |
Uretersigmoid_ostomy |
|
| C |
Prolonged vomiting |
|
| D |
Systemic antacid therapy |
B i.e. Uretersigmoidostomy
A child had repeated vomiting and developed metabolic alkalosis. The treatment given is ‑
| A |
Ringer lactate |
|
| B |
I.V. normal saline and potassium |
|
| C |
ORS |
|
| D |
I.V. Normal saline |
Ans. is ‘b‘ i.e., I.V. Normal saline and potassium
Treatment of metabolic alkalosis due to vomiting or nasogastric suction.
o Most children with metabolic alkalosis have one of the chloride responsive etiology (e.g., vomiting).
o In these situations, administration of sufficeint sodium chloride and potassium chloride to correct volume deficit is necessary to correct metabolic alkalosis.
o Adequate replacement of gastric losses of sodium and potassium in a child with vomiting can minimize or prevent the development of metabolic alkalosis.
o With adequate intravascular volume and a normal serum potassium concentration, the kidney is able to excrete the excess bicarbonate within a couple of days.
| A |
Respiratory alkalosis |
|
| B |
Metabolic acidosis |
|
| C |
Metabolic alkalosis with paradoxical aciduria |
|
| D |
Metabolic alkalosis with alkaline urine |
Ans. is ‘c’ i.e., Metabolic alkalosis with paradoxical aciduria
- Repetitive vomiting leads to hypochloremic, hypokalemic metabolic alkalosis. The urine is alkaline initially but eventually it becomes acidic (paradoxical aciduria)
- Cause of paradoxical aciduria
– Initially the kidney compensate for metabolic alkalosis by reabsorbing hydrogen and chloride ions in exchange for sodium, potassium and bicarbonate. But gradually as the body stores of sodium and especially potassium become depleted, kidney starts retaining these ions in exchange of hydrogen ions. thus the urine becomes acidic and metabolic alkaline state is further aggravated.
Persistent vomiting in G.O.O. causes –
| A |
Hyponatremic hyperchloremia occur |
|
| B |
Hypernatremia without led Cl- alkalosis |
|
| C |
Hypokalemic metabolic alkalosis |
|
| D |
All |
Answer is ‘c’ i.e. Hypokalemic metabolic alkalosis
- Repetitive vomiting leads to hypochloremic, hypokalemic metabolic alkalosis. The urine is alkaline initially but eventually it becomes acidic (paradoxical aciduria)
- Cause of paradoxical aciduria
-
Initially the kidney compensate for metabolic alkalosis by reabsorbing hydrogen and chloride ions in exchange for sodium, potassium and bicarbonate. But gradually as the body stores of sodium and especially potassium become depleted, kidney starts retaining these ions in exchange of hydrogen ions, thus the urine becomes acidic and metabolic alkaline state is further aggravated.
| A |
Metabolic alkalosis |
|
| B |
Respiratory alkalosis |
|
| C |
Metabolic acidosis |
|
| D |
Respiratory acidosis |
Ans. is ‘a’ i.e., Metabolic alkalosis
The commonest cause of metabolic alkalosis is ‑
| A |
Cancer stomach |
|
| B |
Pyloric stenosis |
|
| C |
Small-bowel obstruction |
|
| D |
Diuretics |
Ans. is ‘b’ i.e., Pyloric stenosis
In Accelerated HTN what is metabolic defect:
| A |
Normal non-ionic metabolic acidosis |
|
| B |
Ionic gap metabolic acidosis |
|
| C |
Hypomagnesemia |
|
| D |
Metabolic alkalosis |
The answer is D (Metabolic Alkalosis)
Accelerated Hypertension is associated with metabolic alkalosis.
Accelerated Hypertension is a state in which there is renal underperfusion, high renin, and increased aldosterone. This may result in hypokalemia and metabolic alkalosis.
| A |
Bartter Syndrome |
|
| B |
Gitelman’s Syndrome |
|
| C |
Liddle’s Syndrome |
|
| D |
Renal Tubular Acidosis |
Ans. A (Bartter Syndrome):
Hypokalemic Metabolic Alkalosis with Hypercalciuria in a patient with normal blood pressure suggests a diagnosis of Bartter Syndrome.
|
Presentation |
Diagnosis |
|
Hypokalemic Metabolic alkalosis with Hypertension |
Liddle’s Syndrome |
|
Hypokalemic Metabolic Alkalosis without Hypertension |
Banner Syndrome (Increased Urinary Ca Excretion) Gitelman Syndrome (Decreased Urinary Ca Excretion) |
|
Important Differences Between Bartter Syndrome and Gitelman’s Syndrome |
||
|
Feature |
Bartter Syndrome |
Gitelman Syndrome |
|
Location of kidney defect |
Ascending loop of Henle (Mimics effects of loop diuretics) |
Distal tubule (Mimics effects of thiazides) |
|
Urinary Calcium excretion |
Normal or increased, commonly with nephrocalcinosis |
Decreased |
|
Serum Mg level |
Normal Magnesium levels (Maybe decreased) |
Decreased, sometimes greatly |
|
Renal prostaglandin E2 production |
Increased |
Normal |
|
The usual age at presentation |
Before birth to early childhood, often with intellectual disability and growth disturbance |
Late childhood to adulthood |
|
Neuromuscular symptoms (e.g., muscle spasms, weakness) |
Uncommon or mild |
Common |
| A | Mineralocorticoid deficiency Recurrent vomiting |
|
| B | Bartter’s syndrome | |
| C |
Thiazide diuretic therapy |
|
| D |
Recurrent vomiting |
Ans. is A Mineralocorticoid deficiency
Metabolic alkalosis is seen in all except :
| A |
Thaizide diuretic therapy |
|
| B |
Prolonged vomiting |
|
| C |
Uretero-sigmoidostomy |
|
| D |
Cushing’s disease |
Answer is C (Uretero-sigmoidostomy):
Ureterosigmoidostomy is a cause for normal anion gap type M eta bolic acidosis produced due to loss of bicarbonate in feces. All other options mentioned in the question are causes of metabolic alkalosis.
In a case of hypertrophic pyloric stenosis, the metabolic disturbance is:
March 2004
| A |
Respiratory alkalosis |
|
| B |
Metabolic acidosis |
|
| C |
Metabolic alkalosis with paradoxical aciduria |
|
| D |
Metabolic alkalosis with alkaline urine |
Ans. C i.e. Metabolic alkalosis with paradoxical aciduria
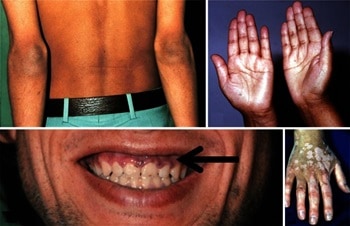
Symptoms of disease shown in Photograph is NOT characterized by
| A |
Hyponatremia |
|
| B |
Hyperkalemia |
|
| C |
Hypotension |
|
| D |
Metabolic alkalosis |
Ans is D Metabolic alkalosis
These are the symptoms of addition’s Disease
Addison’s disease, also known as primary adrenal insufficiency and hypocortisolism, is a long-term endocrine disorder in which the adrenal glands do not produce enough steroid hormones.[1] Symptoms generally come on slowly and may include abdominal pain, weakness, and weight loss. Darkening of the skin in certain areas may also occur. Under certain circumstances, an adrenal crisis may occur with low blood pressure, vomiting, lower back pain, and loss of consciousness. An adrenal crisis can be triggered by stress, such as from an injury, surgery, or infection
