
Metronidazole
| A | Metronidazole | |
| B |
Penicillin |
|
| C |
Tetracycline |
|
| D |
Sulfa drug |
Treatment for Trichomonas vaginalis is :
| A |
Metronidazole |
|
| B |
Penicillin |
|
| C |
Tetracycline |
|
| D |
Sulfa drug |
Metronidazole
Treatment of choice in Gardenella vaginitis in pregnancy :
| A |
Clindamycin |
|
| B |
Metronidazole |
|
| C |
Erthromycin |
|
| D |
Tetracycline |
Metronidazole
Drug of choice for bacterial vaginosis is:
| A |
Metronidazole |
|
| B |
Erythromycin |
|
| C |
Tetracycline |
|
| D |
Nystatin |
- Presence of homogeneous vaginal discharge.
- Presence of amine odor when potassium hydroxide solution is added to vaginal secretions (whiff test).
- Presence of clue cells (>20% of epithelial cells) on microscopy. Clue cells are identified as numerous stippled or granulated epithelial cells.
- Vaginal pH >4.5.
A lady presented with a creamy white vaginal discharge having fishy odour. What is the drug of choice of this condition?
| A |
Doxycycline |
|
| B |
Ofloxacin |
|
| C |
Metronidazole |
|
| D |
Clindamycin |
The clinical scenario is of bacterial vaginosis. Oral treatment with metronidazole-particularly with a 7-day regimen-provides reasonable coverage against both trichomoniasis and bacterial vaginosis, the usual causes of symptoms of vaginal discharge.
Ref: Marrazzo J.M., Holmes K.K. (2012). Chapter 130. Sexually Transmitted Infections: Overview and Clinical Approach. In D.L. Longo, A.S. Fauci, D.L. Kasper, S.L. Hauser, J.L. Jameson, J. Loscalzo (Eds), Harrison’s Principles of Internal Medicine, 18e.
Patient presenting with abdominal pain, diarrhea taking clindamycin for 5 days. Treated with metronidazole symptoms subsided. What is the causative agent –
| A |
Clostridium difficile |
|
| B |
Clostridium perfringens |
|
| C |
Clostridium welchi |
|
| D |
Clostridium marneffi |
Ans. is ‘a’ i.e., Clostridium difficile
A patient presents with lower gastrointestinal bleed. Sigmoidoscopy shows ulcer in the sigmoid. Biopsy from this area shows flask-shaped ulcers. Which of the following is the most appropriate treatment ‑
| A |
Intravenous ceftriaxone |
|
| B |
Intravenous metronidazole |
|
| C |
Intravenous steroids and sulphasalazine |
|
| D |
Hydrocortisone enemas |
Ans. is ‘b’ i.e., Intravenous metronidazole
Flask-shaped ulcer in a patient of GI bleed suggests amebiasis (amoebic dysentry).
Drug therapy for amoebiasis
- Asymptomatic carrier —> Luminal agents (Iodoquinol, Paromomycine) Diloxanide furoate is the DOC.
- Acute colitis —> Metronidazole or Tinidazole + Luminal agent.
- Liver abscess Metronidazol or Tinidazole or ornidazole + Luminal agent.
| A | Fluoxetine | |
| B |
Metronidazole |
|
| C |
Griseofulvin |
|
| D |
b and c |
Ans. is ‘b’ i.e., Metronidazole ‘c’ i.e., Griseofulvin
o Person is presenting with features of disulfiram like reaction which is produced when certain drugs are taken along with alcohol.
o Metronidazole, Griseofulvin and cefoperazone can produce disulfiram like reaction.
Metronidazole is used for all except ‑
| A | Amoebiasis | |
| B | Giardiasis | |
| C |
Trichomonas vaginitis |
|
| D |
Malaria |
Ans. is ‘d’ i.e., Malaria
Metronidazole is used in :
1. Amoebiasis 5. Pseudomembranous enterocolitis.
2. Giardiasis 6. Ulcerative gingivitis, trench mouth.
3. Trichomonas vaginitis 7. H. pylori gastritis, peptic ulcer.
4. Anaerobic bacterial infection
| A |
Pseudomembranous colitis |
|
| B |
Neurocysticercosis |
|
| C |
Giardiasis |
|
| D |
Amebic liver abscess |
Ans. is ‘b’ i.e., Neurocysticercosis
Best drug for anaerobic infections –
| A |
Metronidazole |
|
| B |
Imipenem |
|
| C |
Aztreonam |
|
| D |
a and b |
Ans. is ‘a’ i.e., Metronidazole; ‘b’ i.e., Imipenem
Antibiotics that cover the Anaerobes
1. Penicillin with Beta lactamase inhibitor
- Augmentin (Amoxicillin & Clavulanate)
- Timentin (7icaricillin & Clavulanate)
- Unasyn (Ampicillin & Sulbactam)
- Zosyn & Tazobactam)
2. Second generation Cephalosporins
- Cefoxitin
- Cefotetan
- Cefmetazole
3. Imipenem
4. Chloramphenicol
5. Clindamycin
6. Metronidazole
7. Trovafloxacin
| A |
Ciprofloxacin |
|
| B |
Metronidazole |
|
| C |
Piperacillin |
|
| D |
Clindamycin |
Ans. is ‘b’ i.e. Metronidazole
o Metronidazole is the DOC for clostrdium difficle associated diarrhoea.
o Alternative drugs are vancomycin, fusidic acid, teicoplanin, and bacitracin.
| A |
Intravenous ceftriaxone |
|
| B |
Intravenous metronidazole |
|
| C |
Intravenous steroids and sulphasalazine |
|
| D |
Hydrocortisone enemas |
Ans. is `b’ i.e., Intravenous metronidazole
Lower gastrointestinal bleeding along with the presence of flask shaped ulcers on sigmoidoscopy confirms the diagnosis of intestinal amoebiasis (Amoebic colitis).
|
Drug therapy for Amoebiasis |
|
|
Asymptomatic carrier (Luminal agents) |
|
|
• lodoquinol • Paromomycin |
650 mg t.i.d. for 20 days 500 , ‘0 day.s. |
|
Acute colitis |
|
|
• Metronidazole • plus Luminal agents as above |
750 mg PO or IV tid for 5-10 days |
|
Amoebic liver abscess |
|
|
• Metronidazole or • Tinidazole or • Ornidazole • plus Luminal agent as above |
750 mg PO or IV tid for 5-10 days 2gPO 2 g PO once |
March 2004
| A | Pseudomembranous enterocolitis | |
| B |
Anaerobic bacterial infection |
|
| C |
Amoebiasis |
|
| D |
All of the above |
Ans. D i.e. All of the above
Disulfiram like reaction is commonly caused by which of the following:
March 2005
| A |
Penicillin |
|
| B |
metronidazole |
|
| C |
Tetracycline |
|
| D |
erythromycin |
Ans. B: Metronidazole
Drugs causing Disulfiram like reaction
- Metronidazole
- Cefamandole
- Cefoperazone
- Chlorpropamide
- Sulfonylureas
- Quinacrine
- Griseofuvin
- Chloramphenicol
- Tinidazole
- Procarbazine
- Ritonavir
- Nitrofurantoin
- Chloramphenicol
- Chloral hydrate
Kerala 11
| A | Acamprostate | |
| B |
Metronidazole |
|
| C |
Tetracycline |
|
| D |
Digitalis |
Ans. Metronidazole
Radiosensitising substances include:
| A |
Oxygen |
|
| B |
SR 250 8 |
|
| C |
Metronidazole |
|
| D |
All of the above |
Ans. All of the above
All are uses of metronidazole except ‑
| A |
Amoebiasis |
|
| B |
Giardiasis |
|
| C |
Trichomonas vaginitis |
|
| D |
Malaria |
Ans. is ‘d’ i.e., Malaria
Metronidazole
- It has broad spectrum antiprotozoal activity against trichomonas, E. histolytica and G. lamblia.
- It is also active against many anaerobic bacteria.
- It does not affect aerobic bacteria.
- It acts by inhibiting pyruvate : Ferredoxin oxidoreductase (PFOR) enzyme pathway of pyruvate oxidation in anaerobes.
- In protozoa the mechanism of action is different, i.e. damage to DNA.
- Metronidazole is a nitroimdazole, nitro group is activated by reduction to form reactive cytotoxic product that damages the DNA.
- It inhibit cell mediated immunity to induce mutagenesis and causes radiosensitization.
Uses
- Amoebiasis
- Pseudomembranous enterocolitis.
- Giardiasis
- Ulcerative gingivitis, trench mouth.
- Trichomonas vaginitis
- H. pylori gastritis, peptic ulcer.
- Anaerobic bacterial infection
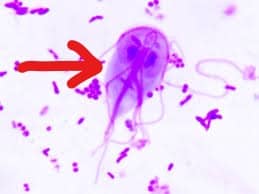
| A | Albendazole. | |
| B |
Praziquantel. |
|
| C |
Metronidazole + Diloxanide. |
|
| D |
Tetracycline. |
Ans:C.)Metronidazole + Diloxanide.
The parasite marked by a red arrow in the photomicrograph above is Giardia lamblia.
Giardia Lamblia
- Giardia lamblia, also known as Giardia intestinalis, is a flagellated parasite that colonizes and reproduces in the small intestine, causing giardiasis.
- The parasite attaches to the epithelium by a ventral adhesive disc, and reproduces via binary fission.
- Giardiasis does not spread via the bloodstream, nor does it spread to other parts of the gastrointestinal tract, but remains confined to the lumen of the small intestine.
- Giardia infection can occur through ingestion of dormant microbial cysts in contaminated water, food, or by the fecal-oral route .
- Under a normal compound light microscope, Giardia often looks like a “clown face”, with two nuclei outlined by adhesive discs above dark median bodies that form the “mouth”. Cysts are oval, have four nuclei, and have clearly visible axostyles.
- Standard treatment for giardiasis consists of Metronidazole with Diloxanide as single use of Metronidazole has been associated with significant failure rates in clearing parasites from the gut and with poor patient compliance.
| A |
Metronidazole and fluconazole |
|
| B |
Metronidazole and azithromycin |
|
| C |
Metronidazole and doxycycline |
|
| D |
Fluconazole only |
Ans.’a’Metronidazole and fluconazole
An elederly male presented with headache, fever and hemiparasis of right side. On further examination and investigation a diagnosis of brain abscess was made. Which of the following antibacterial/ antibacterials is effective in this patient
| A |
Gentamyc in |
|
| B |
Doxycycline |
|
| C |
Streptomycin |
|
| D |
A combination of cephalosporin and metronidazole |
Ans. d. A combination of cephalosporin and metronidazole
- Empirical therapy of community-acquired brain abscess in an immunocompetent patient typically includes a third-or fourth-generation cephalosporin (e.g. cefotaxime, ceftriaxone or cefepime) and metronidazole
- “Optimal therapy of a brain abscess involves a combination of high dose parenteral antibiotics and neurosurgical drainage. Empirical therapy of community-acquired brain abscess in an immunocompetent patient typically includes a third-or fourth-generation cephalosporin (e.g. cefotaxime, ceftriaxone or cefepitne) and metronidazole.”- Harrison 18/e p3429
Brain Abscess
- Intracerebral abscess may occur as a result of direct spread from air sinus infection, following surgery or from hematogenous spread especially associated with respiratory infection, endocarditis or dental infectionQ.
- Increased risk of abscess in: Cyanotic heart disease, immunocompromised (diabetes, solid organ transplant, hematological malignancy or long-term steroids)°
- Organisms: Streptococci (MC), Bacteroides, Pseudomonas, Hemophilus and Enterobacteriaceae
| Etiology | Location |
| Otitis media, mastoiditis | Temporal lobe >Cerebellum |
| Paranasal sinusitis, dental infections | Frontal lobes° |
| Hematogenous | Parietal lobe° |
Clinical Features:
- Presentation is with focal signs, seizures and raised ICP, as with other mass lesions, but the time course is often shortQ.
- Patients may be febrile or have a raised peripheral white cell count or inflammatory markers
Diagnosis:
- CT scan: Ring-enhancing mass lesion (may be multiple in case of hematogenous spread)Q
Treatment:
- Surgical drainage + IV antibiotics for at least 6 weeksQ
- Multiple small abscesses may be treated medically with antibiotics targeted against organisms
Brain Abscess
- Steroids are reserved for cases with significant edema or mass effectQ
- Owing to the Ifgh risk of seizures, patients should also be treated with anticonvulsants
- Optimal therapy of a brain abscess involves a combination of high dose parenteral antibiotics and neurosurgical drainage.
- Empirical therapy ofcommunity-acquired brain abscess in an immunocompetent patient typically includes a third-or fourth-generation cephalosporin (e.g. cefotaxime, ceftriaxone or cefepime) and metronidazole.
| A |
Azithromycin + Metronidazole + Fluconazole |
|
| B |
Azithromycin |
|
| C |
Metronidazole + Fluconazole |
|
| D |
Fluconazole |
Ans. c. Metronidazole + Fluconazole
