
MULTIPLE PREGNANCY – COMPLICATION AND MANAGEMENT
COMPLICATIONS:
Maternal:
During pregnancy:

- Nausea and vomiting
- Anemia
- Pre-eclapmsia (25%)
- Hydramnios (10%)
- Antepartum hemorrhage
- Malpresentation Preterm labour (50%)
- Mechanical distress
During labour :
- Early rupture of membranes and cord prolapse
- Prolonged labour
- Increased operative interference
- Bleeding Postpartum hemorrhage
During puerperium:
- Subinvolution
- Infection
- Lactation failure
- Miscarriage
Fetal
- Prematurity (80%) :main cause of increased mortality and morbidity
- Growth problem (25%)
- Intrauterine death Asphyxia and still birth
Fetal anomalies
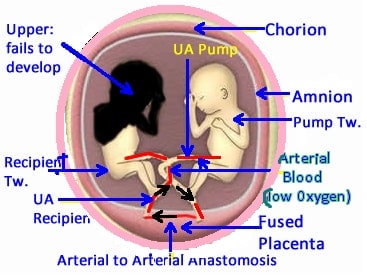
- Twin twin transfusion syndrome (TTS)
- Dead fetus syndrome
- Twin reversed arterial perfusion (TRAP)
- Conjoint twin
- Fetal acardius
- Monoamniocity
Twin twin transfusion syndrome (TTS):
- One twin appears to bleed into other through placental vascular anastomosis.
Receptor twin:
- Becomes larger with hydramnios, polycythemic, hypertensive and hypervolemic
Donor twin :
- Become smaller with oligohydramnios, anemic, hypotensive and hypovolemic.
- Appear stuck
- Difference of hemoglobin concentration:> 5 gm%
- Estimated fetal weight discrepancy: 25%
Management :
- Antenatal diagnosis
- Repeated amniocentesis
- Prevent preterm labour and placental abruption.
- Selective reduction of one twin is done when survival of both the fetuses is at risk.
- Plethoric twin: risk of CCF and hydrops.
- Perinatal mortality: 70%
Dead fetus syndrome:
- Death of one twin (2-7%) associated with poor outcome of the Co-twin (25%) specially in monochorionic placenta.
- The surviving twin runs the risk of cerebral palsy, microcephaly, renal cortical necrosis and DIC.
- Thromboplastin liberated from the dead twin that crosses via placental anastomosis to the living twin.
Twin reversed arterial perfusion (TRAP):
- Characterized by an acardiac perfused twin having blood supply from a normal co-twin via large arterio-arterial anastomosis.
Monoamniocity:
- Monochorionoc twins leads to high perinatal mortality due to cord problems.
- Prostaglandin synthase inhibitor used to reduce fetal urine output, creating borderline oligohydramnios and to reduce the excessive movements
MANAGEMENT:
Antepartum Management:
- Delivery of markedly preterm neonates be prevented
- Fetal-growth restriction identified and afflicted fetuses be delivered before they become moribund
- Fetal trauma during labor and delivery be avoided,
- Expert neonatal care be available.
Diet:
- Increased requirement of calories, protein, minerals, vitamins, and essential fatty acids.
- Caloric should be increased by another 300 kcal/day.
- Supplementation with 60 to 100 mg/day of iron and1 mg/day of folic acid.
- Bed Rest
- Antepartum Surveillance: sonographic examinations
- Tests of Fetal Well-Being
- Prevention of Preterm Delivery (50% incidence)
- Hospitalization
- Use of corticosteroids to accelerate fetal lung maturation
Management during labour:
DELIVERY OF THE FIRST BABY:
- In an uncomplicated twin pregnancy :Vertex delivery
- Forceps delivery: if needed, under pudendal block anaesthesia.
- Clamp the cord at two places and cut it between.
- 8-10 cm of cord is left behind for administration of any drug or transfusion
- The baby should be labeled one
DELIVERY OF SECOND TWIN:
- In an uncomplicated twin pregnancy :second baby transverse lie
- Lie, presentation, size and FHS of the second baby ascertained
Lie longitudinal:
- Step I: Low rupture of membranes, syntocinon, internal examination to exclude cord prolapse.
- Step II: IPoor contraction → 5 units of oxytocin
- Step III:Still delayed, interference done.
Vertex:
- Low down—forcep delivery
- High up—CPD ruled out
- Internal version followed by breech extraction under GA or Ventouse
- Breech: Breech extraction
- Lie transverse: Correct by external version or internal version to cephalic or podalic.
Indication of urgent delivery of second baby:
- Severe vaginal bleeding
- Cord prolapse
- Inadvertent use of IV ergometrine
- First baby delivered under general anesthesia
- Appearance of fetal distress.
The risk of delays:
- Intrauterine hypoxia
- Birth asphyxia
- Sepsis
Indications of caesarean Section:
Obstetric causes:
- Placenta previa
- Severe preeclampsia
- Previous CS
- Cord prolapse
- Abnormal uterine contractions
- Contracted pelvis
For twins:
- Noncephalic presentation:First baby is in transverse lie
- IUGR
- Conjoint twins
- Monoamniotic twins
- Monochorionic twins with TTS
- Weight less than 1500 gm
Exam Important
- Prematurity is the main cause of increased mortality and morbidity in twins.
- Primigravida with twin pregnancy may develop Hydramnios, Pregnancy induced hypertension & Malpresentation
- To say twin discordance the differences in the two twins should be 25% with the larger twin as index
- Incidence of preterm delivery in twin pregnancy is 50%
- Important factor for discordant growth between twins is Twin to twin transfusion
- In an uncomplicated twin pregnancy normal delivery should be attempted in First baby – Vertex and second baby transverse lie
- In twin pregnancy, treatment of choice when first baby is in transverse lie is Cesarean section
- In twin pregnancy delivery by cesarean section is advocated in Monoamniotic twins & Weight less than 1500 gm.
- Oligohydramnios is Not associated with twin pregnancy
Don’t Forget to Solve all the previous Year Question asked on MULTIPLE PREGNANCY – COMPLICATION AND MANAGEMENT
Click Here to Start Quiz
Click Here to Start Quiz

