
Vitamin B12 & Deficiency
Vitamin B12 & Deficiency
VITAMIN B12 (COBALAMIN)
- It is also called as extrinsic factor of castle.
- It contains 4.35% cobalt by weight.
- Corrinoids are cobalt containing weight possessing corrin ring.
- Active form of cobalamin is methylcobalmine and deoxyadenosylcobalamine.
- Coenzyme role of Cobalamine-
a) Isomerisation of methylmalonyl CoA to succinyl CoA-
- methylmalonyl-CoA is accumulated and excreted in urine as methylmalonic acid (methylmalonate) in vitamin B I2 deficieny i.e. methylmalonic aciduria.
b) Conversion of homocystein to methionine-
- Reaction catalyzed by cobalamin-dependent methionine synthase also called 5- methyltetrahydrofolate- homocysteine methyltransferase.
Vitamin B12 Metabolism–
- It is absorbed in Ileum.
- The internal absorption of Vitamin B12 requires intrinsic factor (IF), secreted by parietal cells of the stomach.
Transport of Cobalamin to the target tissues-
- Major Cobalamin transport protein in plasma is Transcobalamin II (TC II).
Sources of Vitamin B12-
- Animal origin only includes meat, eggs, milk and fish.
- Absent in plant foods.
- Synthesized in the intestine by the intestinal flora.
Vitamin B12 Deficiency-
- Vitamin B12 deficiency is caused due to-
- Nutritional- strict vegetarians are at a risk.
- Pernicious anaemia
- Gastric- congenital absence of intrinsic factor or gastrectomy.
- Intestinal- intestinal stagnant loop syndrome, Crohn’s disease.
- Neuropathy- subacute combined degeneration(SCAD), demyelination
- Fish tapeworm
- Deficiency of Vitamin B12 causes folate trap.
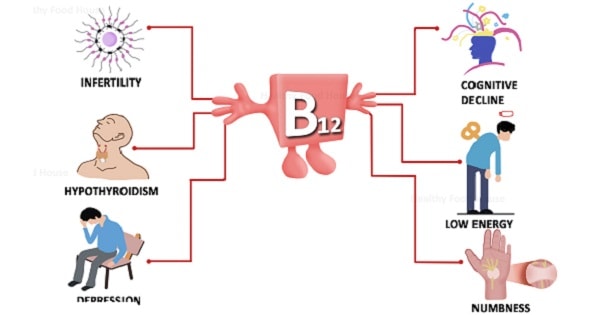
Clinical Manifestations–
- Megaloblastic anaemia
- Homocysteinemia
- Methyl Malonic Aciduria
- Subacute Combined degeneration
- Demyelination
- Corectal scotoma
- Daily Requirement dose-
|
Requirement of vitamin B12 per day |
|
| Healthy adults | 1 mcg |
| Pregnancy | 1.2 mcg |
| Lactation | 1.5 mcg |
| children | 0.2 mcg |

Exam Important
- It is also called as extrinsic factor of castle.
- It contains 4.35% cobalt by weight.
- Corrinoids are cobalt containing weight possessing corrin ring.
- Active form of cobalamin is methylcobalmine and deoxyadenosylcobalamine.
- Coenzyme role of Cobalamine-
a) Isomerisation of methylmalonyl CoA to succinyl CoA-
- methylmalonyl-CoA is accumulated and excreted in urine as methylmalonic acid (methylmalonate) in vitamin B I2 deficieny i.e. methylmalonic aciduria.
b) Conversion of homocystein to methionine-
- Reaction catalyzed by cobalamin-dependent methionine synthase also called 5- methyltetrahydrofolate- homocysteine methyltransferase.
Vitamin B12 Metabolism–
- It is absorbed in Ileum.
- The internal absorption of Vitamin B12 requires intrinsic factor (IF), secreted by parietal cells of the stomach.
Transport of Cobalamin to the target tissues-
- Major Cobalamin transport protein in plasma is Transcobalamin II (TC II).
Sources of Vitamin B12-
- Animal origin only includes meat, eggs, milk and fish.
- Absent in plant foods.
- Synthesized in the intestine by the intestinal flora.
Vitamin B12 Deficiency-
- Vitamin B12 deficiency is caused due to-
- Nutritional- strict vegetarians are at a risk.
- Pernicious anaemia
- Gastric- congenital absence of intrinsic factor or gastrectomy.
- Intestinal- intestinal stagnant loop syndrome, Crohn’s disease.
- Neuropathy- subacute combined degeneration(SCAD), demyelination
- Fish tapeworm
- Deficiency of Vitamin B12 causes folate trap.
Clinical Manifestations–
- Megaloblastic anaemia
- Homocysteinemia
- Methyl Malonic Aciduria
- Subacute Combined degeneration
- Demyelination
Don’t Forget to Solve all the previous Year Question asked on Vitamin B12 & Deficiency

